CPT® 2027 Maternity Care Codes Spark Debate
- By Renee Dustman
- In Coding
- July 31, 2026
- 4 Comments

Big changes are coming to maternity care services coding in CPT® 2027, and this has everyone involved in a tizzy, including the Centers for Medicare & Medicaid Services (CMS).
In the calendar year (CY) 2027 Medicare Physician Fee Schedule (MPFS) proposed rule, published in the July 16 Federal Register, CMS proposes to either adopt the new CPT® codes with a slight change to the American Medical Association’s (AMA’s) code valuations or create new HCPCS Level II codes that would retain current coding and payment structure.
Before we dive into this provision in the CY 2027 MPFS proposed rule, let’s review the CPT® changes to maternity care services.
CPT® 2027 Changes to Maternity Care Services Coding
After more than 30 years, CPT® codes for maternity care services are being restructured from the MMM global period to individual codes.
Why the change?
The AMA says the changes to maternity care coding were necessary to accurately reflect contemporary care. Based on clinical data gathered from industry experts, the AMA determined that maternity care has become increasingly complex and this complexity is not reflected in current coding.
The new coding, according to the AMA, reflects modern, team-based obstetric care; improves transparency, data quality, and measurement; and supports evidence-based labor and postpartum care.
Prior to Jan. 1, 2027, the four phases of maternity care – antepartum, labor management, delivery, and postpartum — were wrapped up into one global package in terms of reimbursement. Beginning Jan. 1, 2027, the global codes for these services are deleted and the four phases of maternity care are reported separately with new or revised codes.
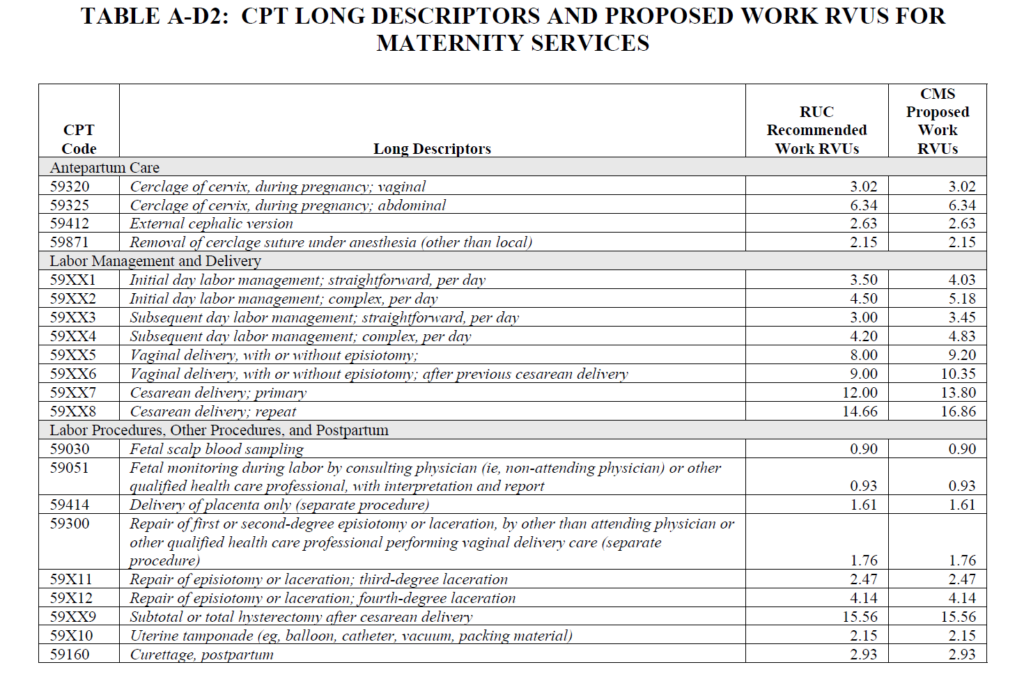
As shown in Table A-D2 in the proposed rule, the restructuring of this subsection in CPT® 2027 resulted in deleting 17 codes, adding 12 codes, and revising six codes. As a result of these changes, there are new subsections and revised guidelines. Some existing codes are relocated, as well.
AAPC the Magazine and Revenue Cycle Insider will cover the maternity care services coding and guideline changes in detail in the coming months, but at least that gives you some context for what CMS is proposing.
What Is CMS Proposing to do About the CPT® Changes?
CMS is on the fence: Should they adopt the CPT® codes and valuations for maternity care determined by the AMA or should they keep everything status quo so as not to rock the boat?
“We have concerns that our adoption of the new [CPT®] codes would be disruptive based on how the longstanding existing code structure is currently accounted for in clinical practice patterns,” CMS states in the proposed rule.
CMS is asking for public comment on whether to:
- Adopt the new CPT® codes for maternity care; or
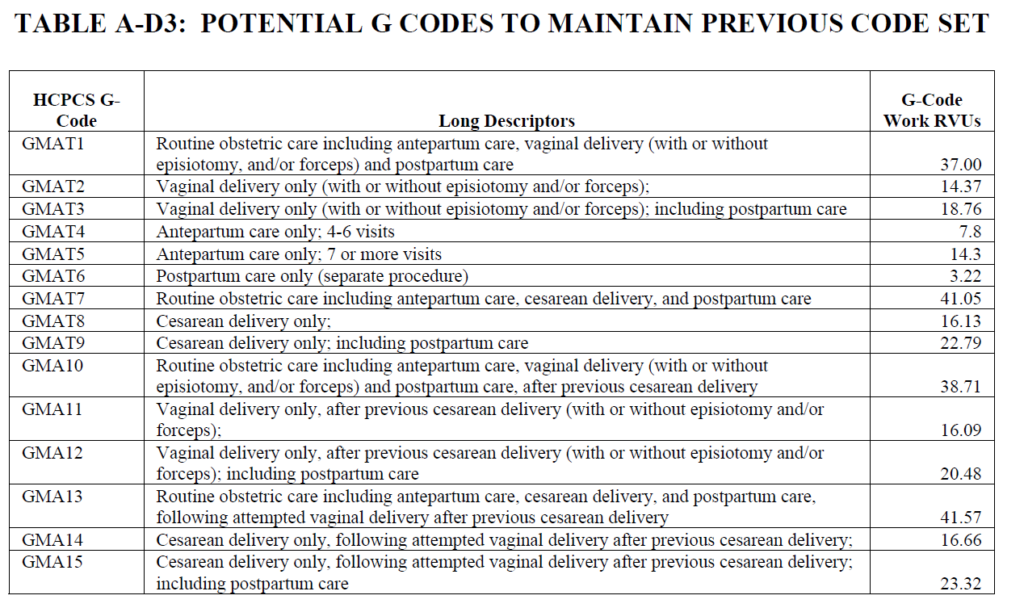
- Create 15 new G codes for CY 2027 that retain the previous MMM global code structure for maternity care services.
As for reimbursement, CMS explains in the proposed rule, the AMA Specialty Society Relative Value Scale Update Committee (RUC) based relative value units (RVUs) for the new codes on 12 prenatal evaluation and management (E/M) visits bundled into CPT® codes 59400, 59510, 59610, and 59618. However, the American College of Obstetricians and Gynecologists (ACOG) now recommends eight visits for average-risk pregnant women and 13 visits for pregnant women with greater-than-average risk.
As such, CMS proposes to remove four evaluation and management (E/M) visits from the utilization estimate calculation and reallocate those RVUs to the new labor and delivery codes. That would reduce the RVUs for the antepartum and postpartum codes, but increase the work RVUs for the labor and delivery codes by 15 percent.
Table A-D3 in the proposed rule shows the CMS proposed work RVUs for the proposed G codes.
Stakeholder Speaks Up
ACOG says that CMS’ proposal to create new G codes “is based on misinformation and incorrect statements.” Determined to set the record straight, the association recently aired the podcast “Updates on Obstetric Codes and Setting the Record Straight” on its website.
Podcast host Lisa Satterfield, lead of the ACOG health and payment policy team, said, “The disappointing part of this rule is that CMS asked for comments about whether or not we should also keep the obstetric global codes.
“It’s not that they’re saying global instead of maternity codes, they’re saying global and maternity codes. And this is not good. This is not good for OB-GYNs, this is not good for patients, it’s not good for maternal outcomes, it’s not good. It pretty much undermines everything that we’ve worked on since 2022.”
According to Satterfield, ACOG surveyed members who overwhelmingly said they want to get rid of the global codes.
“What this does is it introduces the idea that health plans can pick what system they want to use,” Satterfield said about the proposal. “They can pick the new codes, or they can pick the G-code system, the old maternity global codes … it just introduces a lot of chaos and instability.”
Satterfield explained that the intent of the new maternity codes was to have uniform data collection across all payers and health plans. “We don’t need two concurrent coding systems at the same time,” she said.
This may be true, but it’s not unusual for CMS to reject CPT® codes and create new HCPCS Level II codes for reporting the same services when furnished to Medicare beneficiaries. It’s also not unusual for CMS to create HCPCS Level II codes for the sole purpose of bundling services.
Tell CMS What You Think
CMS is soliciting comments on their proposal to create new HCPCS level II G codes in lieu of adopting the new CPT® codes for maternity care services. They are also interested in learning different approaches for how maternity care codes are valued and paid under the MPFS — as opposed to using RUC valuations.
What do you think?
Should CMS create HCPCS Level II G codes that would maintain the current coding and payment for maternity services? Or should CMS adopt the new CPT® codes and reevaluations?
Let CMS know by Sept. 14. Commenting instructions are located at the beginning of the proposed rule.

- COVID-19 Vaccine Pricing for 2026-2027 - September 14, 2026
- Why Healthcare Organizations Need CPC-M™ Coders Now - September 3, 2026
- AMA Revises CPT® Category III Early Release Schedule - August 25, 2026



Leave everything bundled and have one code to use for each over the limit high risk antepartum or post partum visit. Then only one code needs to be tracked for auditing purposes for addt’l visits and doesn’t mess with the RVU’s for everything else.
I would love it, if we code stick with one set of codes that do not run concurrently confusing everyone and potentially creating insurance mishaps and consumer confusion(patients).
Please lets completely convert to the pay as you go newer cpt codes. This stops the process of essentially working for free for 9 plus months with the hope of payment at the end. I think if we are going with the pay as you go codes, we must get rid of the global codes to not increase confusion. The goal of this is to individualize care and to allow practitioners to also reimburse some of their costs as they go rather than hope for reimbursement at the end. Personally I had stopped doing deliveries for about six years and now am back to it in the hope of this code change.
This is my take on the issue. I think we should move forward with the AMA’s new coding system. The global maternity package was somewhat complicated.
My preference would be for CMS to adopt the AMA’s new code set and establish a straightforward, consistent approach for everyone, rather than creating a new set of HCPCS maternity G-codes. I believe this would make the process easier to understand, apply, and administer.