Identify Incision to Slice Your FBR Coding Choices Down
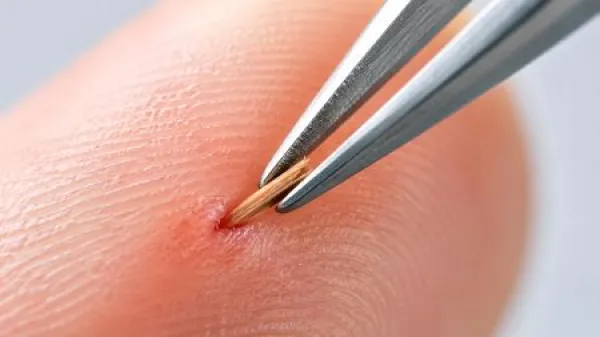
Question: I have an operative report stating that the emergency department (ED) physician performed foreign body removal (FBR) using tweezers. Since the physician had to use tools to remove the foreign body, should I report 10120 for the FBR? Montana Subscriber Answer: No, you should not report 10120 (Incision and removal of foreign body, subcutaneous tissues; simple) for the FBR. In this instance, you would assign the appropriate ED evaluation and management (E/M) code from the 99281-99285 (Emergency department visit for the evaluation and management of a patient …) code set. When the physician performs FBR using only tools such as tweezers, forceps, curettes, etc., it’s an ED E/M service. The physician should set a limit on these types of removal attempts; it could be a time limit, an attempt limit, or an implement limit. They should also be sure to document that they reached these limits. After using certain tools without success, or after trying for a period of time, an incision might be the best approach. When the physician makes an incision, you can report 10120. If the physician makes an incision and then uses other tools such as tweezers or forceps to complete a simple FBR, it’s included in the surgical package for 10120. There’s also the chance that the ED physician performs a complicated FBR. When this occurs, you’ll report 10121 (… complicated). An FBR can be complicated by a number of factors, including what the foreign body is, where it is, and how big it is. If the item is lodged deep into the skin or muscle (for example, a bullet or a large shard of glass), using other means to visualize it might warrant 10121. The way in which the foreign body is lodged may also play into it being more complicated to remove. It might also be close to a major organ or artery or wedged under a bone. Best bet: Look for confirmation of a complicated FBR in the notes. The ED physician’s identification of a complicated FBR should be explicit. Chris Boucher, MS, CPC, Senior Development Editor, AAPC