
Pinpoint the Correct PCN Tube Codes for Placement, Exchange, and Removal
Is imaging guidance included or not? Find out. A percutaneous nephrostomy (PCN) tube is a small, flexible catheter that is inserted through the skin directly into the kidney to drain urine. The tube serves as an alternative pathway for urine flow when the normal drainage system is blocked or compromised as a result of ureteral obstruction, hydronephrosis, malignancy, infection, or complex stone disease. This type of catheter is specifically designed to relieve pressure on the kidney and prevent damage caused by urine buildup on a temporary basis. Accurate coding requires understanding the distinction between new nephrostomy tube placement, nephrostomy tube exchange, and nephrostomy tube removal, as well as recognizing when you can separately report imaging guidance versus when it’s included in the primary procedure code. Know How to Code New Percutaneous Nephrostomy Tube Placement When a physician obtains new percutaneous renal access and places a nephrostomy catheter into the collecting system, report 50432 (Placement of nephrostomy catheter, percutaneous, including diagnostic nephrostogram and/or ureterogram when performed, imaging guidance (eg, ultrasound and/or fluoroscopy) and all associated radiological supervision and interpretation). A key coding principle is that imaging guidance is bundled into 50432. The code also includes the following services: Therefore, you should not report fluoroscopy, ultrasound guidance, or nephrostogram imaging codes separately when billing 50432. Understand Percutaneous Nephrostomy Tube Exchange Coding Patients with chronic nephrostomy tubes often require routine replacement every several weeks to prevent obstruction, encrustation, or infection. When an existing nephrostomy catheter is removed and replaced through the established tract, report 50435 (Exchange nephrostomy catheter, percutaneous, including diagnostic nephrostogram and/or ureterogram when performed, imaging guidance (eg, ultrasound and/or fluoroscopy) and all associated radiological supervision and interpretation). The distinguishing feature is that an established nephrostomy tract already exists; no new renal puncture or access is created. Instead, the provider exchanges one catheter for another through the existing access. Similar to 50432, code 50435 includes the following services: Because these imaging services are included in the descriptor, you should not bill them separately. Recognize How to Report Nephrostomy Tube Removal Nephrostomy tube removal presents a different coding scenario. If the urologist removes a nephrostomy catheter without replacement and without a significant, separately reportable intervention, there is generally no specific standalone CPT® code for the service. Many routine removals are considered part of postoperative or follow-up care and may not generate separate physician reimbursement, depending on the clinical circumstances and payer policy. If removal occurs as part of a more extensive intervention, such as conversion to an internal ureteral stent, you should review the operative documentation and report the definitive procedure that the physician performed. The documentation should clearly support the medical necessity and services rendered. Use Proper Modifiers to Report Bilateral Nephrostomy Procedures When each kidney requires separate access and catheter placement, you’ll report bilateral services with either of the following modifier options, depending on the payer: The documentation should clearly support that the physician placed a distinct nephrostomy catheter in each kidney. Know When Imaging Guidance Is Separately Reportable or Included One of the most common coding errors is reporting imaging guidance separately with nephrostomy procedures. The following services are bundled into nephrostomy codes such as 50432 and 50435: Therefore, coders should not report additional imaging guidance codes along with 50432 or 50435. Dive Into Diagnostic Nephrostogram Codes When the urologist performs a nephrostogram as a truly separate diagnostic study, you’ll report one of the following codes: However, when a provider performs a nephrostogram during a nephrostomy placement or exchange, the procedure is already included in 50432 or 50435 and should not be separately reported. Get to Know Hospital Inpatient vs. Outpatient Coding Considerations In the hospital outpatient and ambulatory surgical center (ASC) settings, providers and facilities typically report 50432 for a new nephrostomy placement and 50435 for a nephrostomy exchange. Both codes include imaging guidance and diagnostic contrast studies performed during the procedure. Facility and professional claims should follow payer-specific billing requirements. For inpatient admissions, the physician coding principles remain the same: Use 50432 for new nephrostomy access with catheter placement and assign 50435 for an existing nephrostomy catheter exchanged through established tract. The fact that the patient is admitted does not change CPT® code selection. The determining factor is whether the physician created new renal access or used existing access. Hospital facility reimbursement will generally occur through the applicable Medicare Severity Diagnosis Related Group (MS-DRG) methodology rather than outpatient ambulatory payment classification (APC) payment systems. Remember These Documentation Tips To support compliant coding for nephrostomy procedures, providers should clearly document the following: If the documentation is missing any of the information above or it is unclear, query the provider for confirmation. Conclusion Correct nephrostomy coding depends on identifying whether the procedure involved a new catheter placement (50432) or an exchange of an existing nephrostomy tube (50435). Both codes are comprehensive services that already include imaging guidance, nephrostography when performed, and radiological S&I. Separate reporting of fluoroscopy, ultrasound guidance, or nephrostogram codes is generally inappropriate unless a distinct diagnostic study is performed independent of the placement or exchange procedure. Understanding these distinctions helps reduce denials, improve compliance, and ensure accurate reimbursement across both hospital inpatient and outpatient settings. Stephanie N. Stinchcomb Storck, CPC, CPMA, CUC,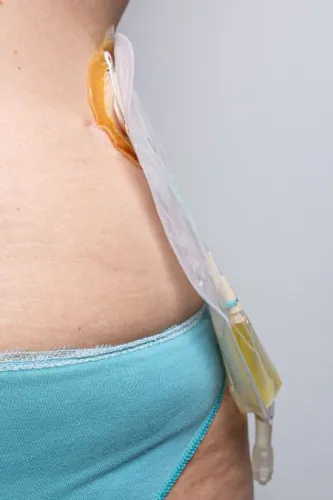
CCS-P, Contributing Writer, Summerfield, Florida
