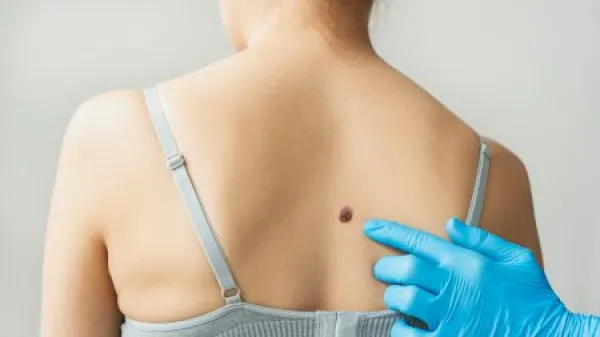
Code What You Know Today — Not What the Results May Tell You Tomorrow
Don’t let anticipation cloud your coding. In the outpatient setting, ICD-10-CM requires you to code to the highest degree of certainty known for that encounter. A biopsy — or any diagnostic test — is often performed precisely because no one knows the answer yet. Think about that for a moment: If the provider already knew the answer, they probably wouldn’t be ordering the test, obtaining the culture, or performing the biopsy in the first place. Focus on the Date of Service When diagnostic testing is performed, the results may ultimately provide a definitive diagnosis. But those results do not change what was known on the date the service was performed. The diagnosis you report should therefore reflect what the provider knew, observed, and documented at that time — not what a test, culture, or pathology report tells you several days later. This is where documentation matters. Questions you need answered include: Those answers establish the clinical reason for the service and give coders the information needed to select the diagnosis that appropriately supports medical necessity on that date of service. Put the Documentation to Work You don’t know the answer yet — so what do you code? The rule behind the reasoning: The ICD-10-CM Official Guidelines for Coding and Reporting instruct outpatient coders not to code diagnoses documented as “probable,” “suspected,” “questionable,” “rule out,” or similar terms. Instead, you should code to the highest degree of certainty for the encounter. Consider the following documentation: Skin: 7 mm irregularly shaped pigmented lesion of the left upper back with asymmetric borders and variation in pigmentation. Patient and parent report the lesion has increased in size and become noticeably darker over the past six months. No bleeding, pain, or pruritus. Given the interval change in size and pigmentation and irregular appearance on examination, biopsy recommended for further evaluation. Specimen obtained and submitted for pathology. Now coders know what is present, where it is located, what it looks like, how it has changed, and why the provider determined a biopsy was necessary. The documentation provides a lot of information, but you don’t have a definitive diagnosis. The provider has not diagnosed melanoma, a dysplastic nevus, a benign nevus, or even a neoplasm. These conditions may be part of the differential, but they have not been established. Based on the documentation available today, L98.9 (Disorder of the skin and subcutaneous tissue, unspecified) is supportable. The diagnosis code does not need to predict what pathology will eventually find. It needs to accurately represent the condition known and documented on the date the provider performed the biopsy. Don’t Forget the Procedure Code Knowing why the provider performed the biopsy isn’t enough to select the CPT® code. You also need to know how they obtained the tissue. Suppose the provider also documented the following: After informed consent was obtained, the area was cleansed and anesthetized with local anesthetic. A 4 mm punch biopsy was performed through the lesion. The specimen was submitted for pathology. Hemostasis was achieved and the site was closed with one simple interrupted suture. For a single lesion obtained by punch biopsy, CPT® code 11104 (Punch biopsy of skin (including simple closure, when performed); single lesion) is appropriate. A tangential or incisional biopsy would require a different CPT® code. The diagnosis documentation tells you why and the procedure documentation tells you how; you need both to code the service correctly. When pathology results come in a few days later, the following documentation becomes available: Pathology: Dysplastic (atypical) melanocytic nevus with moderate atypia. No evidence of melanoma. Now you know something you didn’t know before. At a subsequent encounter, the provider might document the following: Pathology from recent punch biopsy reviewed with patient/parent. Results demonstrate a moderately dysplastic melanocytic nevus of the left upper back without evidence of melanoma. Results discussed and Dermatology follow-up recommended. The documentation now supports a more specific diagnosis. Because the confirmed melanocytic nevus is located on the upper back, you can appropriately report D22.5 (Melanocytic nevi of trunk) for the subsequent encounter. The patient didn’t suddenly develop the nevus when the pathology report came back — your degree of diagnostic certainty changed. Know the 1 Rule and Its Many Applications This concept goes beyond pathology. A wound culture obtained today may identify methicillin-resistant staphylococcus aureus (MRSA) several days from now. A send-out laboratory test may establish a diagnosis that wasn’t known when the specimen was collected: Diagnostic testing gives you new information. Code what you know today and let the results guide what you’ll know tomorrow. Donna Walaszek, CCS-P, Northampton Area Pediatrics, Northampton, Massachusetts